Treatment-Resistant High Blood Pressure: Causes, Evaluation and Care Options
When blood pressure stays high despite several medicines, checking readings, treatment barriers and possible underlying causes can help guide care.
Blood pressure that remains above target despite several medicines can be discouraging. But “treatment-resistant” describes how hard it is to control; it doesn’t mean treatment has failed or that the condition can’t improve. A closer review may uncover inaccurate readings, practical obstacles with a medication plan, a contributing health condition or a combination of factors.
Clinicians generally use the term when blood pressure remains above goal despite three types of medicine at appropriate, often maximally tolerated, doses. The usual combination includes a thiazide or thiazide-like diuretic, a long-acting calcium channel blocker, and either an ACE inhibitor or an angiotensin II receptor blocker (ARB). A person whose blood pressure is controlled only with four or more medicines may also be described as having resistant hypertension.
That definition is separate from whether the cause is known. Primary hypertension has no single identifiable medical cause; age, genetics and lifestyle can all contribute. Secondary hypertension has a specific underlying cause, such as kidney disease or a hormone disorder. Either kind can be difficult to control.
First, make sure the problem is truly resistant
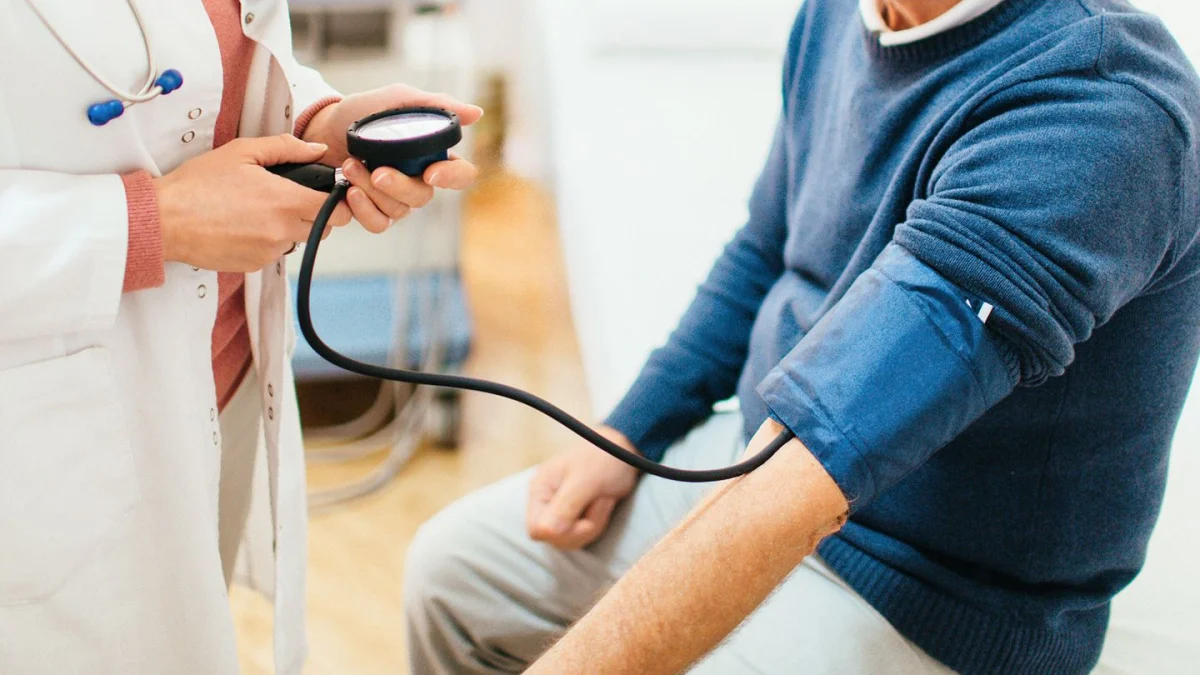
Before settling on a diagnosis, the care team checks for “pseudoresistance”—when readings suggest that treatment isn’t working as expected, but another explanation may be involved. A cuff that is too small, poor positioning or other measurement problems can produce misleading readings. Blood pressure may also run high in a clinic while being lower at home, a pattern known as the white-coat effect.
Home readings can help clarify what’s happening. A clinician can check that a home monitor is reliable and review how readings are taken and recorded. In some cases, a person may wear a portable monitor for 24 hours. It takes readings throughout the day and night, giving the care team a picture beyond a single appointment.
A full medication review is another part of the evaluation. The clinician may ask about prescribed medicines, doses and timing, as well as side effects, supplements and nonprescription products. Taking medicines as prescribed can be difficult when a plan is complicated, expensive or hard to tolerate. Sharing those difficulties helps the care team understand the situation and consider changes that may be easier to manage. Bringing medicine containers or photos of their labels can make the review more accurate.
What can keep blood pressure high?
Several medical conditions can play a part. The tests a clinician considers depend on a person’s history, symptoms and initial findings; not everyone needs every test.
- Primary aldosteronism: The adrenal glands make aldosterone, a hormone that helps regulate how much sodium and water the kidneys retain. Too much aldosterone can lead the kidneys to hold on to more sodium and water, increasing fluid in the blood vessels and raising blood pressure. Blood tests measuring aldosterone and renin, another hormone, can help screen for this condition. High aldosterone alongside low renin may prompt further testing. Low potassium can also raise suspicion, since excess aldosterone can cause the body to lose potassium in urine.
- Obstructive sleep apnea: During sleep, the airway repeatedly narrows or closes, interrupting breathing and sometimes lowering oxygen levels. These episodes activate the body’s stress response and can tighten blood vessels. A sleep study, at home or in a sleep lab, can record breathing, oxygen and other measurements to check for sleep apnea.
- Chronic kidney disease: Healthy kidneys remove excess water and waste. When kidney function is impaired, fluid may build up and contribute to high blood pressure. The relationship also runs in the other direction: high blood pressure can damage the kidneys, making control more difficult. Blood tests such as creatinine measurements and urine tests for protein, blood or other abnormalities may help assess kidney health.
- Narrowed arteries supplying the kidneys: Renal artery stenosis reduces blood flow to the kidneys. In response, the kidneys may activate systems that make the body retain salt and water and narrow blood vessels. Plaque buildup is one possible cause. If a clinician suspects this problem, imaging such as a Doppler ultrasound may be considered; kidney imaging may also be used to look for other abnormalities.
- Other hormone disorders: An overactive or underactive thyroid can affect blood pressure. Less common causes include Cushing syndrome, in which the body makes too much cortisol, and pheochromocytoma, a rare adrenal tumor that releases excess hormones such as adrenaline. Thyroid or other hormone tests may be appropriate based on the clinical picture.
Medicines and supplements can also raise blood pressure or interfere with treatment. Examples include nonsteroidal anti-inflammatory drugs (NSAIDs), such as ibuprofen and naproxen; some birth control pills, particularly those with higher estrogen doses; and stimulants used to treat attention deficit hyperactivity disorder, such as methylphenidate. Decongestants and some supplements or herbal products—including licorice root, bitter orange and yohimbine—may also contribute. Anyone who uses these products can discuss their effects and possible alternatives with a clinician or pharmacist, rather than changing a prescribed treatment on their own.
Everyday factors can matter, too. Excess sodium encourages the body to retain water, and much of the sodium people eat comes from packaged or restaurant food. Heavy alcohol use can affect the nervous system and hormones involved in blood pressure regulation. Obesity can activate nerves and hormones that tighten blood vessels and increase sodium retention; it also raises the risk of sleep apnea.
Treatment depends on what the review finds
If testing points to an underlying condition, addressing it is often part of the plan. Treating sleep apnea, for example, may involve a continuous positive airway pressure (CPAP) machine that helps keep the airway open during sleep. Kidney, artery and hormone conditions each call for an approach suited to the specific finding.
The medication plan may also need adjusting. A clinician might review nonprescription products or supplements that affect blood pressure, or discuss alternatives if a person regularly uses an NSAID. For blood pressure medicines, the choice of combination and dose depends on the readings, test results, response and side effects. In some cases, a longer-acting diuretic such as chlorthalidone may be considered.
If blood pressure remains high on the usual three-medicine combination, a clinician may consider a medicine that blocks aldosterone’s effects. Spironolactone is one example; it helps the kidneys release extra sodium and water. It can also raise potassium, so the care team commonly checks potassium and kidney function before and during treatment. The source article also describes baxdrostat as an add-on option, but its date and approval claim cannot be confirmed here; readers can ask their clinician or pharmacist about current treatment options.
Habits can support medical treatment
Daily habits may contribute to better control and, for some people, reduce the number of medicines needed. They don’t replace prescribed treatment. Goals are best discussed with a care team, especially when kidney disease, other conditions or medication effects affect what is safe.
- Pay attention to sodium: The source describes aiming for less than 1,500 to 2,000 milligrams a day depending on a person’s care plan, while citing a general limit below 2,300 milligrams, ideally closer to 1,500. Restaurant meals, fast food, canned soups, deli meats and processed foods can be significant sources. Nutrition labels can help when comparing products.
- Consider the DASH eating pattern: The Dietary Approaches to Stop Hypertension plan emphasizes vegetables, fruit, whole grains, beans, nuts and low-fat dairy. Leafy greens, beets and berries contain plant compounds that may help blood vessels relax.
- Ask about potassium before making major changes: Foods such as cantaloupe, kiwifruit, potatoes and spinach contain potassium. Potassium can help the body remove sodium, but too much in the blood can cause dangerous heart rhythm problems. People with kidney disease or taking medicines that raise potassium can ask their care team how much is suitable.
- Stay active as health allows: The source cites a goal of at least 150 minutes of moderate activity each week, such as brisk walking. If weight loss is appropriate, a clinician can help shape a plan around a person’s health and routine.
- Review alcohol use, sleep and stress: Alcohol can raise blood pressure. The source cites general American Heart Association limits of no more than two drinks a day for men and one for women. Sleep and stress strategies such as paced breathing, meditation, yoga or tai chi may also be worth discussing.
Some supplements, including magnesium, omega-3 fatty acids and aged garlic extract, may have small benefits alongside treatment, according to the source. Others can raise blood pressure or interact with medicines, and supplements aren’t a substitute for prescribed care. Before adding one, discuss its possible benefits, risks and interactions with a healthcare professional or pharmacist.
When specialist care may help
A hypertension specialist is a physician with focused expertise in difficult-to-control blood pressure. Specialists may be cardiologists, kidney doctors or internists with additional training. A referral may be useful when blood pressure remains high despite several medicines, side effects make treatment difficult, a kidney or hormone cause is suspected, high blood pressure began at a young age, or there are signs of heart or kidney damage. A specialist may also be involved when a procedure is being considered.
One such procedure is renal denervation. A specialist guides a thin catheter through a blood vessel to the arteries supplying the kidneys, then uses energy to reduce activity in nearby nerves that can raise blood pressure. It may be considered for some people whose blood pressure remains uncontrolled. It works alongside medicines and lifestyle changes; a specialist can explain its potential benefits and risks in light of an individual’s situation.
Even without symptoms, uncontrolled high blood pressure can increase the risk of heart attack, stroke, heart failure, kidney disease and dementia over time. Persistent high readings, difficulty tolerating medicines, or questions about supplements and nonprescription products are reasons to bring the details to a clinician or pharmacist. Resistant hypertension can take careful investigation, but it can still be treated.