Retatrutide Outperformed Semaglutide for Weight Loss in a Type 2 Diabetes Trial
In an 80-week study of about 1,300 adults, retatrutide led to greater weight loss and a larger average A1C reduction than semaglutide.
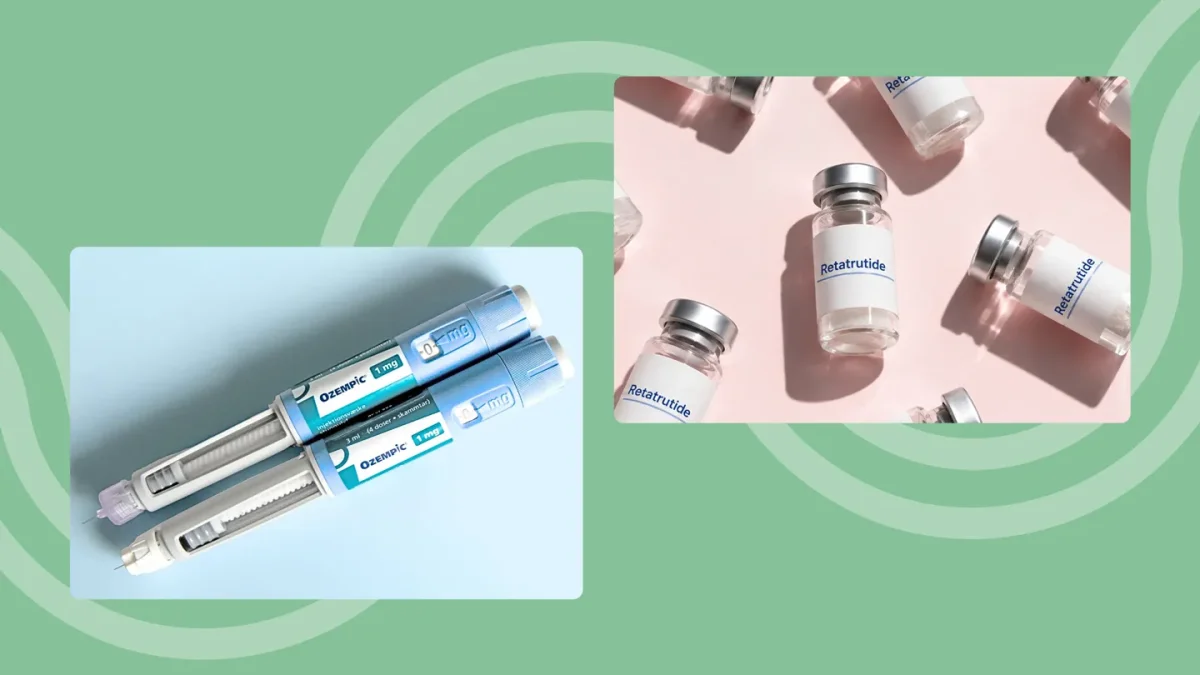
Retatrutide produced substantially greater average weight loss than semaglutide in an 80-week study of adults with type 2 diabetes, while also lowering A1C more. The results come from a late-stage, randomized comparison, but they don’t establish how retatrutide would compare with every available treatment or how well its results hold up over longer periods.
The study, called TRANSCEND-T2D-2, enrolled about 1,300 adults. Participants were assigned to weekly injections of either 9 milligrams or 12 milligrams of retatrutide, or 2 milligrams of semaglutide, the active ingredient in Ozempic. That semaglutide dose was the highest approved for that medication in the United States at the time described in the report.
Weight loss and blood sugar results
After 80 weeks, people taking 9 milligrams of retatrutide had lost an average of 44 pounds, about 20 percent of their starting weight. The average loss for the 12-milligram group was about 47 pounds. Participants taking semaglutide lost an average of 21 pounds, or roughly 9 percent of their starting weight.
A1C, a measure that reflects average blood sugar over roughly two to three months, fell by an average of 2.2 percentage points in both retatrutide groups. In the semaglutide group, it fell by 1.8 percentage points. The differences describe group averages; they don’t predict what any one person would experience.
The company also reported greater improvements with retatrutide in several measures linked with heart health: non-HDL cholesterol, triglycerides, and systolic blood pressure. Those measures can help describe changes in risk factors, but the information provided does not show that retatrutide prevented heart attacks, strokes, or other complications.
A different approach to hormone signaling
Semaglutide acts on the GLP-1 receptor. Retatrutide activates three hormone receptors: GLP-1, GIP, and glucagon. This is why it is sometimes described as a triple agonist. For comparison, tirzepatide, the active ingredient in Mounjaro and Zepbound, acts on GLP-1 and GIP receptors.
These hormone signals affect appetite and digestion. Retatrutide is given as a weekly injection and may also affect how much energy the body uses. That broader activity offers one possible explanation for the larger weight loss seen in this comparison, but the trial result alone doesn’t show which receptor contributed how much.
Doctors interviewed about the findings said earlier research had already suggested that retatrutide could lead to substantial weight loss, so the new results were not unexpected. One noted that a comparison with tirzepatide could help clarify whether adding the glucagon receptor target improves results beyond a two-receptor approach. TRANSCEND-T2D-2 compared retatrutide with semaglutide; it did not answer that question.
Side effects and treatment limits
Digestive effects, including diarrhea and vomiting, were reported more often with retatrutide than with semaglutide. The report describes most side effects as mild to moderate and says they generally eased before the study ended. Some effects were more common at the higher retatrutide dose, although the available account does not provide a complete breakdown of individual side effects.
More participants stopped treatment in the 12-milligram group: about 8 percent, compared with about 5 percent in the 9-milligram group and 3 percent among those taking semaglutide. These figures offer one measure of how treatment was tolerated during the study, but they don’t explain every participant’s reason for stopping.
The doctors quoted in the report emphasized that medicines for obesity are generally considered for people with substantial weight-related health needs, rather than as a way to lose a small amount of weight. They also pointed out that weight often returns when treatment ends. This makes long-term care and follow-up relevant when weighing potential benefits, side effects, and a person’s broader health needs.
What the results mean for patients
Retatrutide remains experimental and is not available for routine use in the United States outside clinical studies. The manufacturer said it plans to seek US authorization for obesity treatment in the first quarter of 2027, with a submission for type 2 diabetes to follow during 2027. Those plans do not guarantee when, or whether, the medicine will become available.
For now, the findings add evidence that retatrutide can reduce weight and A1C in adults with type 2 diabetes, but they don’t establish its long-term safety or show that it is the right option for a particular person. Anyone considering weight or diabetes treatment can discuss current choices, expected follow-up, and possible side effects with a doctor or pharmacist. Further comparisons and longer-term results will help put retatrutide’s place among these medicines into clearer view.